NICU Monitoring Failures: Delayed Response to Apnea, Bradycardia, and Oxygen Desaturation
Apnea, bradycardia, and oxygen desaturation are common in neonatal intensive care, particularly among premature infants. Some events resolve without treatment. Others require stimulation, supplemental oxygen, respiratory support, medication, or more advanced intervention depending on the baby’s condition.
A poor outcome does not automatically mean that NICU staff provided negligent care. The important questions are whether the medical team appropriately monitored the infant, recognized clinically significant deterioration, and responded in a timely and appropriate manner.
What Are Apnea, Bradycardia, and Oxygen Desaturation in a Newborn?
Apnea is a pause in breathing. Premature infants are particularly susceptible because the systems controlling breathing may not yet be fully developed.
Bradycardia means the baby’s heart rate has fallen below the expected range. Apnea and bradycardia can occur together because interrupted breathing may affect oxygen levels and heart rate.
Oxygen desaturation, often called a “desat,” occurs when the oxygen saturation measured in the baby’s blood falls below the desired range.
These events do not all have the same clinical significance. NICU clinicians must consider how long an event lasts, how severe it is, whether it resolves spontaneously, whether similar episodes are becoming more frequent, and what else is happening with the baby’s condition.
When Can NICU Monitoring Become a Patient-Safety Problem?
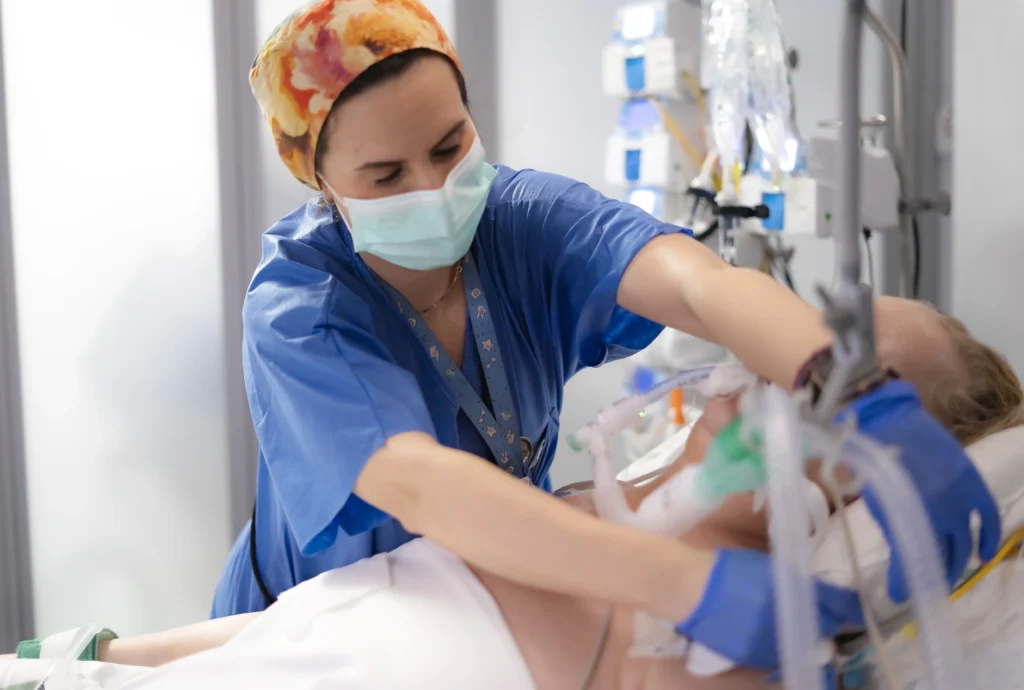
Continuous monitoring only protects a newborn when the systems surrounding that monitoring work.
Potential failures may include:
- Alarm limits that are not appropriately set for the infant
- Alarms that are silenced, disabled, or improperly adjusted
- Failure to recognize repeated or worsening episodes
- Delayed bedside assessment after a significant alarm
- Failure to escalate concerns to a physician or neonatal provider
- Inadequate respiratory support after deterioration
- Failure to investigate the cause of recurring apnea, bradycardia, or desaturation
- Poor communication during nursing or physician handoffs
- Inadequate surveillance of a high-risk infant
- Disconnection, displacement, or malfunction of monitoring equipment
Hospitals also need policies addressing alarm settings, who can modify alarms, how staff respond when alarms activate, and how monitoring equipment is maintained.
The problem in a potential NICU negligence case may therefore extend beyond one nurse or physician. The investigation may also examine staffing, communication, hospital policies, alarm-management practices, and whether the system reliably brought significant changes in a newborn’s condition to the attention of someone who could intervene.
Alarm Fatigue Can Complicate NICU Monitoring
NICU monitors can generate a large number of alarms, including those that do not ultimately require treatment. Repeated exposure to alarms can make it more difficult for clinicians to distinguish urgent warnings from nonactionable signals, a problem commonly referred to as alarm fatigue.
That does not, by itself, make a delayed response acceptable or establish negligence. It does mean that hospitals need effective systems to identify clinically significant alarms and ensure that the appropriate caregiver responds.
In a serious injury investigation, questions may include whether the alarm was audible, whether it reached the assigned caregiver, whether alarm parameters were appropriate, and how long it took for someone to assess the infant.
When Does Delayed Intervention Become Concerning?
The presence of apnea, bradycardia, or oxygen desaturation does not, by itself, establish medical malpractice. These events can occur even when an infant receives appropriate care.
The concern changes when a significant event or a worsening pattern appears on the monitor, but the response does not match the baby’s clinical condition.
Important questions may include:
- How long did the event last?
- How low did the baby’s heart rate or oxygen saturation fall?
- Were episodes becoming longer, deeper, or more frequent?
- Did the bedside or central monitor generate an alarm?
- Who received the alarm?
- How quickly did someone assess the baby?
- Did the infant require stimulation, oxygen, CPAP, positive-pressure ventilation, intubation, or another intervention?
- Were earlier episodes documented?
- Was a physician or neonatal specialist notified?
- Were monitor settings changed or alarms silenced?
- Did clinicians investigate why the events were recurring?
- Did the baby’s condition require a higher level of respiratory or medical support?
Recurring apnea, bradycardia, or desaturation may also signal another medical problem that requires evaluation. When infection is suspected, for example, respiratory changes and unstable vital signs can be part of a broader picture of neonatal sepsis or meningitis. The legal question in a NICU monitoring case, however, remains focused on whether clinicians recognized the deterioration and responded appropriately.
What Records Can Show Whether a NICU Responded Appropriately?
A serious NICU monitoring case requires more than just reviewing a discharge summary or a physician’s progress note.
The investigation may require comparison of:
- Bedside and central-monitor data, when available
- Heart-rate and oxygen-saturation trends
- Alarm histories and logs
- Nursing flowsheets
- Respiratory therapy records
- Medication administration records
- Physician and neonatal provider notes
- Orders for oxygen and respiratory support
- Blood-gas and laboratory results
- Resuscitation or rapid-response documentation
- Electronic medical record timestamps
- Staffing and assignment records
- Hospital alarm policies and NICU protocols
These records may establish what the monitor showed, when a caregiver became aware of the problem, what intervention followed, and whether the baby’s condition continued to deteriorate.
That distinction matters because documentation in a progress note may not capture every event reflected in continuous physiological monitoring.
A detailed review should therefore compare the electronic data with the clinical chart rather than rely on a single source.
Can Delayed NICU Intervention Cause Brain Injury?
Severe or prolonged disruption of oxygen delivery can injure a newborn’s developing brain and other organs. Depending on the circumstances, oxygen deprivation may be associated with seizures, developmental impairment, cerebral palsy, or hypoxic brain injury.
But causation requires careful analysis.
A monitor alarm does not establish that a newborn suffered brain damage, nor does it prove that an earlier response would have prevented an injury. Experts may need to determine how long oxygenation or circulation was compromised, how severe the event was, whether there were repeated episodes, and whether another condition caused or contributed to the injury.
When oxygen deprivation is suspected, the evaluation may overlap with issues involving hypoxic-ischemic encephalopathy or cerebral palsy and hypoxic brain injury.
Experts may also need to distinguish an injury that developed in the NICU from an injury caused before or during delivery. That distinction can materially affect both the medical analysis and the potential liability theory.
When Can a NICU Monitoring Failure Support a Medical Malpractice Claim?
A NICU monitoring claim requires more than proof that an alarm sounded or that a newborn experienced a complication.
The investigation must determine whether the providers responsible for the baby’s care met the applicable standard of care and whether any failure to do so caused or worsened the child’s injury.
Potential issues can include:
- Failure to appropriately monitor a high-risk newborn
- Failure to recognize recurrent or worsening events
- Delayed response to clinically significant alarms
- Failure to escalate care
- Delayed respiratory intervention
- Improper alarm management
- Communication failures between nurses, physicians, and respiratory therapists
- Hospital policies or staffing practices that contributed to a delayed response
These cases can involve both individual clinical decisions and broader questions of hospital negligence.
They may also require neonatologists, pediatric neurologists, respiratory specialists, nursing experts, biomedical or monitoring system experts, and other specialists to determine what happened and whether a different response would likely have changed the outcome.
The analysis falls within the broader evaluation of prenatal, birth, and neonatal injury claims, but the focus is specific: what did the monitoring show, who knew about it, what did they do, and was the response timely enough for the baby’s condition?
When a NICU Emergency Raises Questions About the Response
Parents may leave the NICU knowing that their baby experienced repeated “desats,” bradycardia, apnea, resuscitation, or an unexpected deterioration without knowing what the monitors showed before the injury or how quickly the medical team responded.
McEldrew Purtell evaluates catastrophic prenatal, birth, and neonatal injury cases involving inadequate monitoring, delayed intervention, hypoxic brain injury, and hospital negligence. A detailed investigation can compare monitor data, nursing documentation, respiratory records, provider notes, and hospital policies to determine whether warning signs were recognized and addressed appropriately.
Families whose child suffered a catastrophic neonatal injury or death can contact McEldrew Purtell for a free consultation.